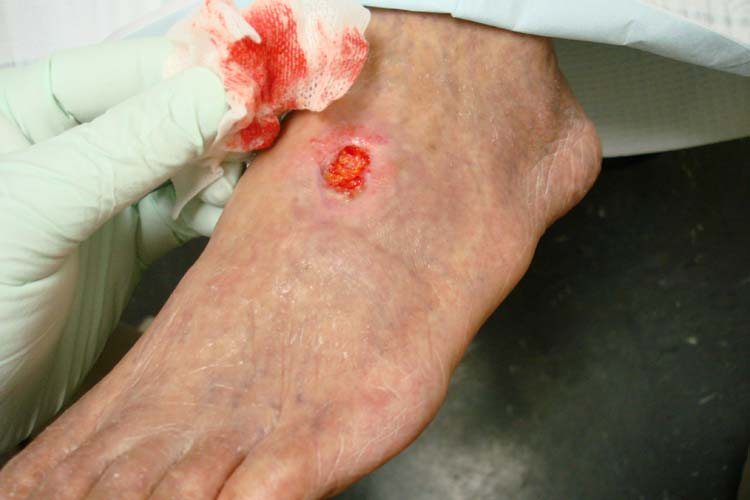
Peripheral arterial disease is routinely described as a local disease of the legs and, particularly when it produces no symptoms, as relatively benign. Both characterizations are inaccurate, according to a new editorial published in The Lancet. The condition is caused by atherosclerotic narrowing of the arteries supplying the limbs, but it is better understood as one visible manifestation of systemic atherosclerosis — a process that affects the entire vascular system, not just the lower extremities.
The clinical picture is further complicated by how the disease presents. When symptoms do appear, they are frequently attributed to ageing or to musculoskeletal disease rather than to vascular insufficiency. Only a minority of patients report the classical intermittent claudication — exertional leg pain that is relieved by rest — that clinicians are taught to search for during evaluation. That mismatch between the textbook presentation and real-world experience means many cases are likely missed or misclassified.
The editorial's central argument is that how peripheral arterial disease is counted and characterized matters for how it is treated. Framing the condition as a benign, localized problem of the legs can lead to underdiagnosis and undertreatment, even though the underlying atherosclerotic process carries broader cardiovascular risk. Because the disease reflects systemic atherosclerosis, patients with peripheral arterial disease are at risk from cardiovascular events beyond the limbs, and the editorial suggests that clinical attention should reflect that reality.
The diagnostic gap described in the editorial is consistent with evidence from large-scale imaging research. A separate study of more than 16,000 apparently healthy adults found that more than half had signs of atherosclerosis, with arterial plaques already detectable in roughly 1 in 13 people between the ages of 18 and 29. The researchers behind that work concluded that directly imaging the arteries could reveal hidden cardiovascular disease years or even decades before symptoms appear.
Taken together, the two lines of evidence point to a common problem: atherosclerosis often develops silently long before it produces the symptoms that bring patients to a doctor. In the case of peripheral arterial disease, the symptoms that do eventually emerge may be atypical or attributed to other causes, making clinical recognition even less reliable. The editorial's call to reconsider how the disease is counted is therefore not a semantic exercise. It reflects a concern that current assumptions about the condition's nature and severity may be shaping practice in ways that leave patients underrecognized and undertreated.
For clinicians, the practical implication is that peripheral arterial disease should not be dismissed as a benign or purely local problem. The editorial emphasizes that it is a marker of systemic atherosclerotic burden, and that the absence of classic intermittent claudication does not mean the disease is absent or inconsequential. Improving how the condition is identified and counted — rather than relying on the classical symptom pattern alone — is presented as a necessary step toward addressing the gap between what the disease actually is and how it is commonly perceived.
11